RytmoECG
EN PL
Get it

Polar H10 · iPhone · on-device

Your Polar H10, read like an ECG strip.

The chest strap you already own streams a 130 Hz single-lead ECG. RytmoECG draws it at true ECG paper scale and reads every beat on the phone.

Wellness app, not a medical device. Requires a Polar H10, iOS 17 or later.

Polar H10 style chest strap on a dark surface

Strap on

Wet the electrodes, clip the sensor, open the app.

No pads, no wires. The H10 pairs over Bluetooth and the strip starts in seconds.

Move

Run, lift, sleep.

The strap keeps reading while you move.

Motion becomes a trace

Every step, one line.

HR
... bpm
RMSSD
... ms
Events
0

    A real recording from the owner's strap. Wellness data, not a medical device.

    Try it

    Live demo, no install.

    Pick a sample rhythm and watch simplified versions of the app's algorithms run on it in your browser. No cloud round-trip; the analysis is computed from the strip you see.

    LEAD I · 130 Hz · Clean sinus
    HR
    ...
    bpm
    RMSSD
    ...
    ms
    SDNN
    ...
    ms
    QTc
    ...
    ms
    VERDICT
    ...

    The demo runs simplified versions of the same detectors that ship in the app. Real signal from your strap gives more nuance; here we use synthetic but physiologically plausible rhythms. The last option is different: a real excerpt from the owner's Polar H10, replayed at true speed, with the auto-events the app raised on that recording.

    Holter mode · PDF report

    What your doctor gets.

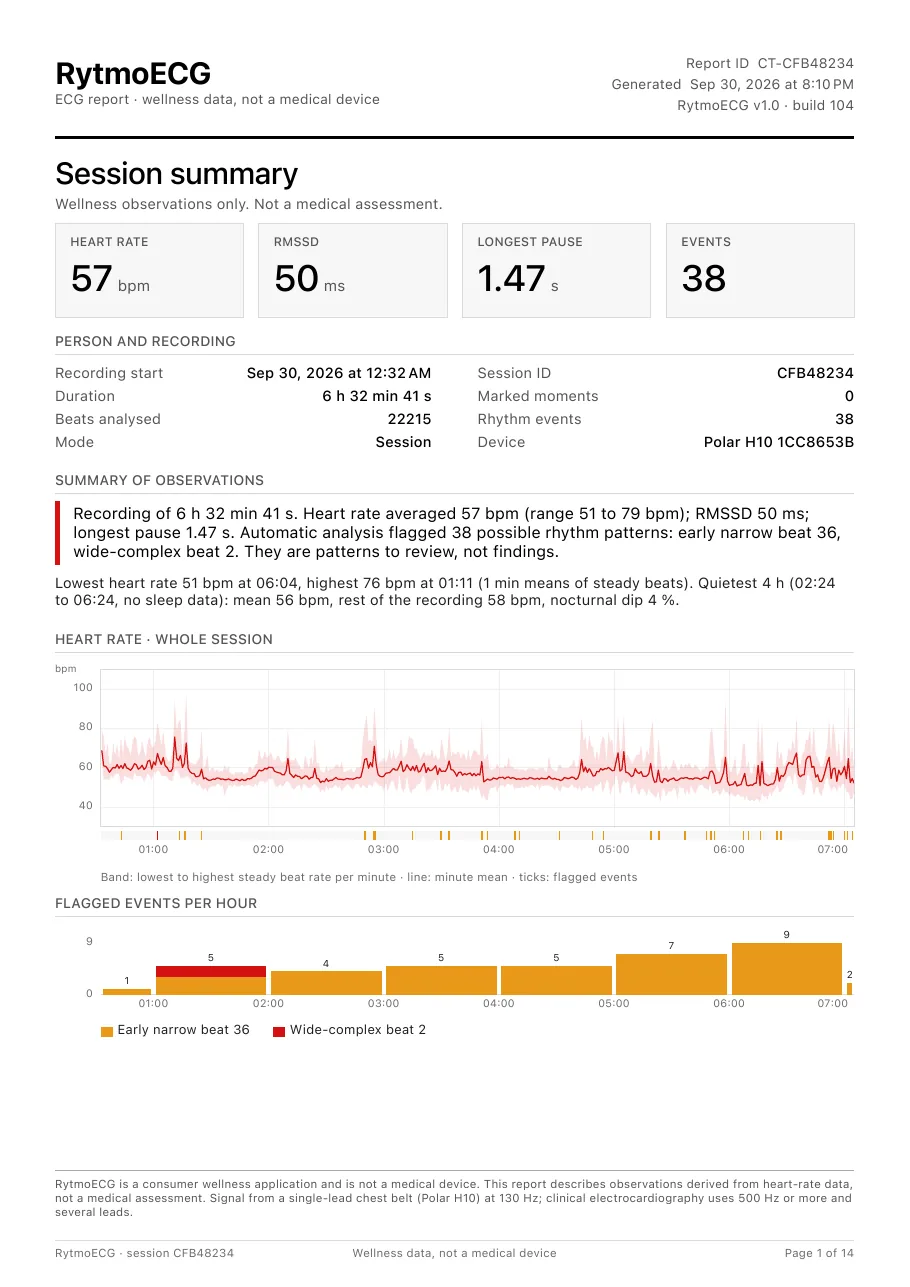
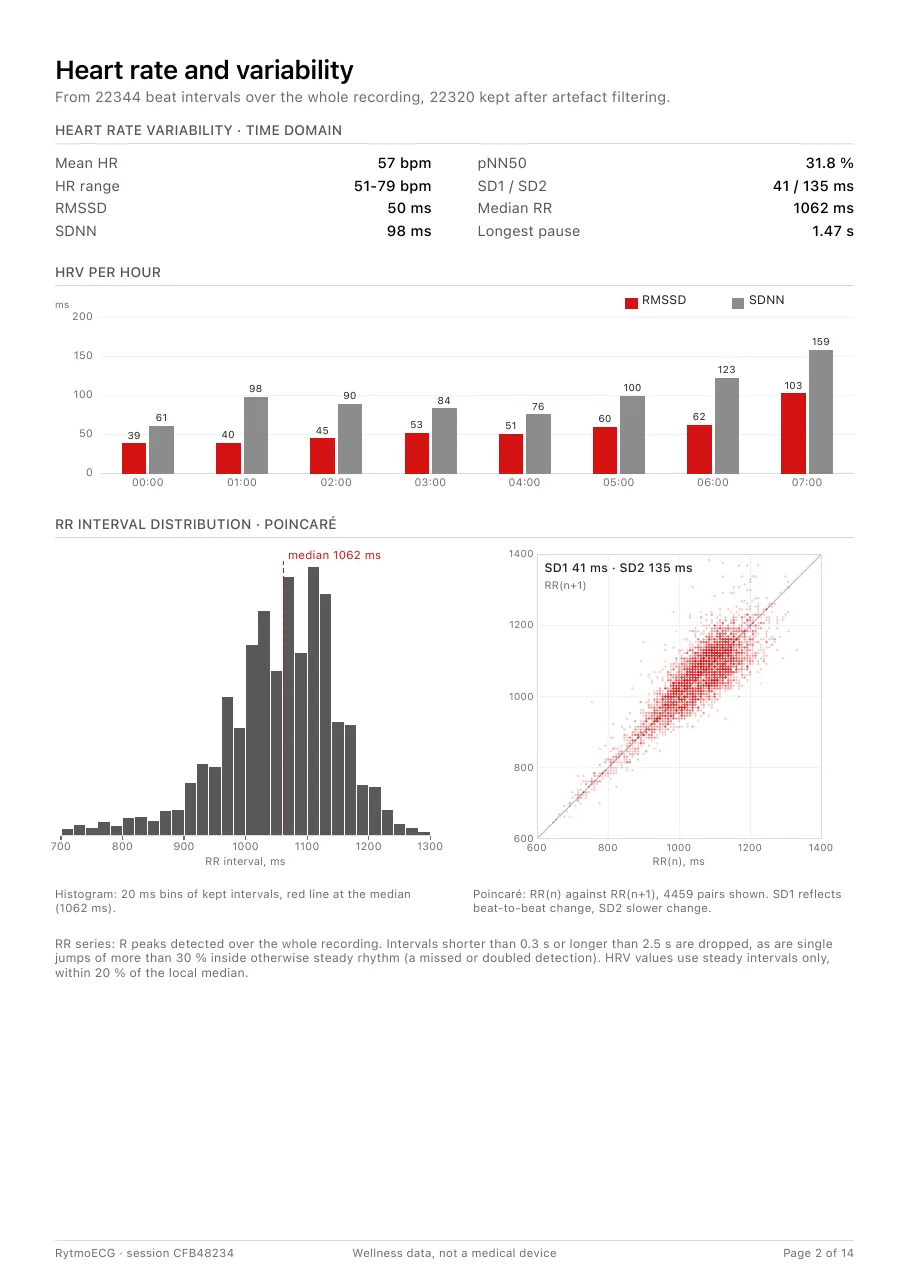
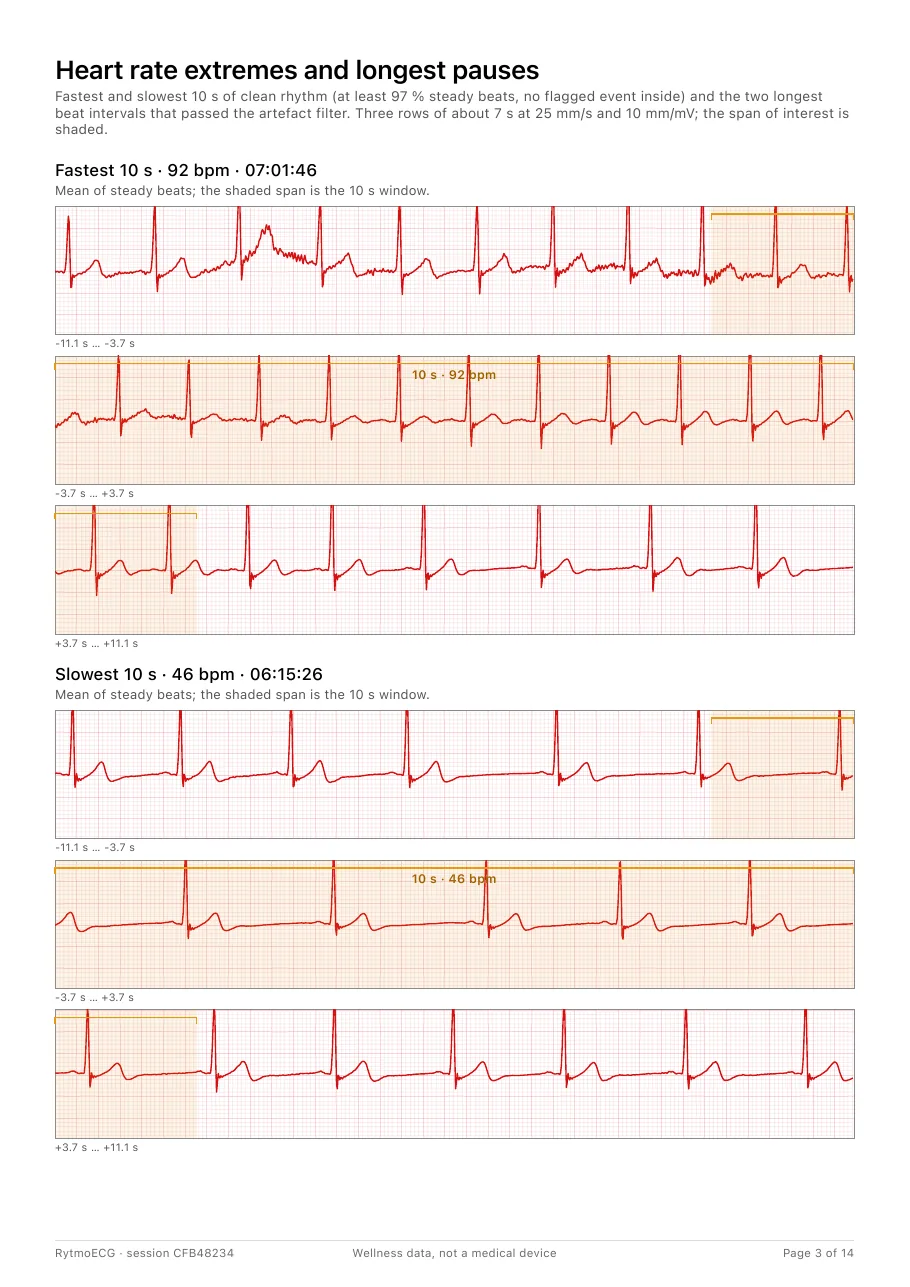
    Record overnight or for 24 hours with a Polar H10, then export one PDF. These pages come from a real 6 h 33 min night, unedited.

    See the full sample report
    1. Report page 1: session summary with heart rate over the night and flagged possible patterns per hour
      01One-page summary: heart rate over the night, possible patterns per hour.
    2. Report page 2: heart rate variability per hour, RR interval histogram and Poincare plot
      02Variability, RR histogram, Poincaré.
    3. Report page 3: fastest and slowest 10 seconds of the night as ECG strips at 25 mm/s
      03The fastest and slowest 10 seconds and the longest pauses, on real 25 mm/s paper.

    The pipeline

    Raw chest-strap signal, fifteen stages, zero cloud.

    The Polar H10 streams 130 samples per second of single-lead ECG. RytmoECG takes that buffer end-to-end on your iPhone. Nothing leaves the device unless you tap Share.

    01BLE stream130 Hz lead I + accelerometer + battery
    02Pan-TompkinsStreaming R-peak detector with adaptive thresholds
    03Per-beat featuresMorphology, amplitude, premature flag, SQI
    04Rolling HRVRMSSD, SDNN, pNN50, Poincare SD1/SD2
    05Rhythm patterns10+ rhythm pattern detectors
    06Core ML AFCNN-BiLSTM trained on PhysioNet CinC 2017
    07QT analyzerT-wave tangent method per beat
    08BiomarkersDC, AC via PRSA; HRT after PVCs
    09Movement gateAccelerometer std-dev, three states
    10Event captureChained recording with a 10-second clean-rhythm tail
    11HRV spectrum4 Hz RR resample + Hann window + vDSP FFT → LF / HF / VLF
    12Non-linear HRVDFA alpha1 / alpha2 + Sample Entropy on RR
    13Breathing rateHF peak frequency × 60
    14HR zones + driftTime-in-zone Z1-Z5; cardiac drift slope
    15Wellness scoresStress + Readiness vs 30-day personal baseline

    Anatomy of one heartbeat

    P, Q, R, S, T; and every interval RytmoECG measures.

    Every cardiac cycle is a five-wave story; atria depolarize, ventricles depolarize, ventricles repolarize. The intervals between them are what separate a healthy rhythm from one worth investigating. RytmoECG measures each one and labels them honestly.

    P Q R S T PR 120 to 200 ms QRS 60 to 100 ms QT 380 to 440 ms 25 mm/s · 10 mm/mV · 1 large box = 200 ms
    ECG at standard paper speed; each small grid square = 40 ms × 0.1 mV. RytmoECG measures the R-R series for HRV, the QRS width for morphology, and the QT interval (corrected per Fridericia) for repolarization.

    P wave

    Atrial depolarization. Roughly 80 to 120 ms wide, under 0.25 mV. Single-lead chest-strap geometry makes the P-wave unreliable; RytmoECG does not separate atrial flutter from AF for that reason.

    QRS complex

    Ventricular depolarization. Normal width 60 to 100 ms; wide complex above 120 ms suggests ventricular origin or bundle branch block. RytmoECG flags wide-complex beats as possible PVCs.

    T wave

    Ventricular repolarization. We locate T-end with the tangent method (Lepeschkin & Surawicz 1952); the slope of the descending limb is extrapolated to the isoelectric line.

    PR interval

    Atrioventricular conduction time. Outside 120 to 200 ms suggests block or pre-excitation. RytmoECG does not flag the PR interval automatically (the P wave is noisy on a single lead); we surface it inside Advanced Analysis as a measurement, not a flag.

    QT interval

    Total duration of ventricular depolarization and repolarization. Strongly HR-dependent. RytmoECG reports the running median of the last two hundred beats; corrected via Fridericia (QT / RR^1/3), which holds up better than Bazett at the extremes of HR.

    RR interval

    The time between successive R-peaks; the rolling RR-series is the input to every HRV metric we publish. PVC and SQI rejection ensure a single artifact does not corrupt the trend.

    What it notices

    Ten rhythm patterns, one ML atrial-fibrillation model.

    Each strip below is the exact shape the detector looks for. We capture fifteen seconds of ECG before the event from a ring buffer, then keep recording until ten seconds pass with no further event. If another event fires in that window, the recording extends; you get one clip of the whole burst, with a tally like "bigeminy × 9 · couplet × 2".

    Possible patterns, never verdicts. Every card below is something to observe and, if you want, to show a clinician with the saved clip.

    Sinus rhythm

    baseline

    What it is. Regular rhythm originating in the SA node. RR intervals tight, narrow QRS, T-waves upright. RytmoECG shows "Steady" when this holds.

    How we detect it. RR coefficient of variation under 6 %, no wide complexes for thirty consecutive beats, irregular detector silent.

    PVC (premature ventricular contraction)

    wide complex

    What it is. A beat that fires early from a ventricular focus. Wide (> 120 ms), bizarre morphology, often followed by a compensatory pause.

    How we detect it. Beat classified wide-complex by the morphology classifier, prematurity flagged (RR shorter than 92 % of the running median, so at least 8 % early), then pause classifier checks whether pre-RR + post-RR sums to ~2 × baseline (PVC) or ~1.85× (PAC).

    Couplet

    two consecutive

    What it is. Two consecutive wide-complex beats. More electrically irritable than a singleton PVC.

    How we detect it. Two wide-complex beats back-to-back, both premature relative to baseline.

    Bigeminy

    alternating pattern

    What it is. Every other beat is ventricular. Normal-PVC-normal-PVC pattern sustained for many cycles.

    How we detect it. Pattern detector sees the N-V-N-V cadence sustained over at least eight beats with stable RR intervals between the singletons.

    Trigeminy

    every third

    What it is. Every third beat is a PVC. Common with caffeine, stress or electrolyte shifts.

    How we detect it. N-N-V cadence sustained for three full cycles (nine beats minimum); cooldown twenty seconds.

    NSVT (non-sustained VT)

    4 to 30 consecutive

    What it is. Four or more consecutive ventricular beats but lasting under thirty seconds. On a clinical Holter, this is a run a cardiologist would review; RytmoECG flags it as possible and keeps the clip.

    How we detect it. Four or more wide-complex beats in a row; the capture window automatically extends until ten seconds pass with no further event.

    Atrial fibrillation (Core ML)

    irregularly irregular

    What it is. Atria fibrillate; ventricles respond irregularly. No P-waves, chaotic baseline, RR intervals "irregularly irregular".

    How we detect it. CNN-BiLSTM with attention pooling trained on PhysioNet CinC 2017 (F1 0.81 holdout); runs every five seconds on the last thirty seconds of ECG, ensembled with the rules-based irregular detector.

    Long pause

    RR > 2.0 s

    What it is. A gap between heartbeats exceeding two seconds. Can be benign (vagal tone) or significant (sinus arrest, AV block).

    How we detect it. Any RR interval > 2.0 s after PVC exclusion. Captured as a discrete event so you can see what came before and after.

    Sustained irregularity

    RR variability

    What it is. RR intervals vary widely without a fixed pattern, but morphology stays narrow. Can reflect breathing-linked sinus variation at high amplitude or another irregular rhythm; worth showing a clinician if it recurs.

    How we detect it. RR coefficient of variation > 12 % sustained over twenty beats with narrow QRS throughout.

    PAC (premature atrial contraction)

    no comp pause

    What it is. An early beat from an atrial focus. Narrow QRS (unlike a PVC), often morphologically distinct, no full compensatory pause.

    How we detect it. Premature beat with narrow QRS, then compensatory-pause classifier rules out PVC; ratio of pre-RR + post-RR to 2 × baseline below 0.95.

    QT interval, in detail

    The tangent method, drawn at last.

    Finding the end of the T-wave by eye is notoriously fiddly; the canonical workaround is to extrapolate the tangent of the descending T-wave limb down to the isoelectric line. RytmoECG does this per beat, rejects beats with SQI below 0.70, and reports the running median of the last two hundred beats.

    QT is highly heart-rate dependent. RytmoECG shows the Fridericia correction by default (QT / RR ^ 1/3); the Bazett correction is available in Advanced Analysis. On a noisy single-lead 130 Hz signal we treat QTc as a trend marker only, not a clinical QTc.

    T-peak T-end (tangent + 40 ms offset) QT
    T-peak located in a 150 to 400 ms window after the R-peak; tangent of the descending limb extrapolated to baseline; forty-millisecond offset added for QRS-onset compensation.
    RR(n) ms RR(n+1) ms SD2 (long-term) SD1 (short-term)
    Each dot is one beat plotted (RR_n, RR_n+1). A tight ellipse aligned with the identity line means a regular rhythm. AF spreads the dots into a starburst; PVCs sit far off the diagonal.

    HRV · Poincaré plot

    Heart rate variability, drawn instead of summarized.

    The Poincare plot is the most honest HRV visual; each beat is a point on a scatter. SD1 (perpendicular spread) reflects short-term parasympathetic variation. SD2 (spread along the identity line) reflects long-term tone.

    RytmoECG renders this live as a Canvas on the dashboard; you see ectopic beats fly off the diagonal in real time. AF turns the cluster into a starburst; breathing-linked sinus variation stretches the ellipse along SD2 without widening SD1.

    RMSSD, SDNN, pNN50 and the plot itself are built from normal-to-normal intervals only, so an early beat and its pause do not inflate the number. Comparisons are only with your own baseline, never with other users.

    All algorithms, all references

    Twenty-plus detectors, one paper for each.

    Each measurement is computed on-device. We show what it means, how RytmoECG computes it, the reference paper, and where it can fail. The same content lives inside the app on the Methodology page.

    The catalog

    Every other algorithm that ships in the app. Same depth on the Methodology page inside; this is the index.

    Heart rate (meanHR)

    bpm

    How. Rolling mean of 60 / RR over the last sixty beats; min and max gated by a five-beat warmup.

    Reference. LITFL ECG rate interpretation.

    HRV (RMSSD, SDNN, pNN50, pNN200)

    ms / %

    How. Task Force 1996 standard on PVC-rejected, SQI-filtered RR series. RMSSD = root mean square of successive RR differences; SDNN = std of all NN; pNN50 / pNN200 = share of successive differences > 50 / 200 ms.

    Reference. Task Force ESC / NASPE, Circulation 1996; Shaffer & Ginsberg PMC5624990.

    QRS duration

    ms

    How. Per beat, Q-onset is located by back-search from R-peak; S-end by forward-search; both stop when the signal returns within a 50 uV band of the baseline. Width = (S-end - Q-onset) / sampleRate. Rolling median over the SQI-filtered series.

    Limits. Single lead at 130 Hz; we use baseline-return rather than slope-onset because the latter is noise-sensitive at this rate.

    J-point amplitude

    uV

    How. Voltage 20 ms after S-end, baseline-subtracted, converted to microvolts. Session mean over the SQI-filtered beats.

    Limits. A wellness proxy for ST-segment level; not a clinical ST measurement on a single lead.

    T-wave polarity

    %

    How. For each beat, classify the largest T-extremum (150-400 ms after R-peak) as positive or inverted relative to baseline. meanTPositive = % of positive T-waves over the session.

    Spectral 2-8 Hz energy (meanHF)

    %

    How. Real-input FFT via Accelerate vDSP on a power-of-two slice of the 30 s ECG ring buffer; Hann window applied to reduce leakage. The metric is the ratio of in-band power to total power, refreshed every five seconds.

    Limits. Non-specific; reflects rapid fluctuations of any origin (sharp QRS energy, motion, noise). Useful to compare conditions on the same subject; not clinical.

    Signal amplitude (meanSystole)

    uV

    How. Exponential moving average of mean |sample| in microvolts. A simple "is the strap making good contact today?" marker.

    Poincare SD1 / SD2

    ms

    How. Scatter of (RR_n, RR_n+1); SD1 = std perpendicular to identity, SD2 = std parallel. Rendered live.

    HR exertion (HR span)

    bpm

    How. Smoothed instantaneous HR series (window of five beats), max minus min. Descriptive, requires no user input.

    HREI (TRIMP-Banister)

    load

    How. HR reserve = (avgHR - restHR) / (maxHR - restHR), clamped to [0, 1]. HREI = duration_minutes × HR_reserve × sex_factor (1.92 male, 1.67 female). Enter your details under Personal in Settings; without them the metric uses generic defaults.

    Reference. Banister, E.W. Modeling Elite Athletic Performance, 1991.

    HR recovery

    bpm

    How. Drop from peak HR to lowest HR in the sixty seconds that follow the peak. Standard fitness signal for vagal reactivation.

    Reference. Cole et al., NEJM 1999.

    Signal Quality Index

    0..1

    How. Default-to-trust; score starts at 1.0, only deducts for clear-cut problems (implausible amplitude, baseline drift, off-physiology RR). Rolling mean of last thirty beats shown as the Signal pill.

    Movement gate

    three states

    How. Two-second std-dev of accelerometer magnitude. Thresholds: standstill < 0.04 g, light < 0.15 g, moving ≥ 0.15 g.

    HRV frequency-domain (LF / HF / VLF)

    ms² / ratio

    How. RR-series resampled to 4 Hz with linear interpolation, Hann-windowed, real-input FFT via Accelerate vDSP. Power integrated per Task Force 1996 bands: VLF 0.0033-0.04 Hz, LF 0.04-0.15 Hz, HF 0.15-0.40 Hz. LF/HF ratio published as the autonomic-balance metric.

    Reference. Task Force ESC / NASPE, Circulation 1996.

    Breathing rate from RSA

    /min

    How. Free byproduct of the HRV spectrum: the dominant frequency inside the HF band corresponds to breathing-linked sinus variation. Multiply by sixty for breaths per minute. Typical 10-20 /min at rest.

    DFA alpha1 / alpha2

    scaling exponent

    How. Detrended Fluctuation Analysis on the integrated mean-removed RR series. Linear fit slope of log(fluctuation) vs log(box size) for short scales (4-16 beats, alpha1) and long scales (16-64 beats, alpha2). The endurance community uses alpha1 = 0.75 as a heuristic for the first lactate threshold.

    Reference. Peng et al., Chaos 1995; Rogero, Gronwald et al. 2020.

    Sample Entropy + ApEn

    nats

    How. Non-linear complexity of the RR series. SampEn = -ln(matches at m+1 / matches at m), m=2, r=0.2 × SD. ApEn computed similarly. Lower values mean more regular rhythm; high entropy is associated with healthy variability.

    Reference. Richman & Moorman, AJP-Heart 2000; Pincus, PNAS 1991.

    HR drift

    bpm per 10 min

    How. Linear regression of smoothed instantaneous HR over the session. Reported as drift rate plus R^2 so you know how steady the workload actually was. Smaller drift at sustained effort = better aerobic fitness.

    Stress & Readiness scores

    0..100

    How. Both computed from a 30-day baseline of your own sessions, never anyone else's. Stress = mean of three normalized inputs (RMSSD drop, resting HR rise, LF/HF rise). Readiness = RMSSD lift (60 %) + resting HR low (40 %). Every input is shown next to the score; no black box.

    Sleep HRV cross-section

    via HealthKit

    How. Pulls sleep windows from HealthKit, buckets each RytmoECG session as "night" or "day", and reports the median RMSSD and HR per bucket. Healthy autonomic recovery shows higher RMSSD overnight than during the day; we make the gap visible.

    Pre / post workout HRV

    Δ RMSSD

    How. For each HealthKit workout, locate the nearest RytmoECG session within 8 h before and 12 h after. Report the delta RMSSD so you can see whether the bout left your vagal tone elevated, depressed, or unchanged.

    Calendar heatmap

    365 days

    How. GitHub-style 53 × 7 cell grid; each cell is one day, color-coded by your chosen metric (RMSSD, mean HR, or session count). A year of recording visible without scrolling. Tap to switch metric.

    HR zones (Z1-Z5)

    % maxHR · time in zone

    How. Five-zone breakdown by percent of personal maxHR (set in Settings). Each beat contributes its RR interval to the matching zone; per-session bars show time and percent for each. Standard endurance-coaching layout.

    CSV export

    research format

    How. Every session can be exported as plain CSV: time_seconds, rr_seconds, hr_bpm, sqi per beat, plus a header comment block with sample rate, device, and timestamp. Drop straight into Python / R / MATLAB.

    Advanced Analysis per event

    verdict

    How. Re-runs every detector against a single thirty-to-sixty-second strip in isolation; lists all parameters with flag colors. Verdict: possible irregular pattern, ambiguous, likely normal, or poor signal.

    Privacy

    No account. Nothing leaves the phone.

    • No user accounts, no sign-in.
    • Every algorithm runs on your iPhone. There is no cloud server we control.
    • Nothing is uploaded unless you tap Share to export a PDF, CSV or EDF.

    Apple Watch

    Your Watch recordings, next to your strap sessions.

    ECG strips recorded natively on Apple Watch are read from Apple Health, only with your consent, and shown on the same paper scale as the strap.

    The Watch app can also record heart rate and the strap signal locally and hand them to the paired iPhone.

    Three personas, one app

    Same compute, three skins.

    RytmoECG computes everything for everyone, but a researcher, an everyday user and an athlete want very different things foregrounded. Pick a display mode in Settings; the dashboard re-arranges around what matters to you. Nothing is hidden from view, only reprioritized.

    ∑

    Researcher

    Maximum density. The default.

    • All metrics on Now, formulas inline.
    • HRV spectrum + DFA / Sample Entropy pinned.
    • Tap any tile for the paper + failure mode.
    • CSV / EDF exports one swipe away.
    ♥

    Everyday

    Simplified Now. Plain answers, fewer numbers.

    • HR + rhythm summary only on the front screen.
    • "Looks steady" or "Worth recording" plain copy.
    • Show-to-doctor PDF one tap from any event.
    • Detector jargon out of sight.
    ⏱

    Athlete

    Training emphasis. Zones up front.

    • Live HR zone widget on Now.
    • HR drift + recovery + HREI surfaced.
    • HRV trends pinned for daily readiness.
    • HealthKit cross-check with your workouts.

    The mode does not change what is computed. Every detector runs the same way regardless of skin; we are not hiding numbers from the everyday mode, just not putting them where you would have to look at them.

    How RytmoECG avoids false alarms

    Three gates before any auto-event fires.

    Most wellness apps that flag rhythm patterns get noisy fast: poor signal, movement artifacts and respiratory sinus variation all fake textbook patterns. RytmoECG stacks three guards on top of every detector so you do not get spammed with "low signal · maybe PVC" alerts.

    1. Movement gate

    accelerometer

    If on-strap accelerometer std-dev is above 0.15 g (active movement) over the last two seconds, all auto-event capture is suppressed outright. Light motion (0.04 to 0.15 g) reduces confidence by 25 %.

    2. Hard SQI gate

    signal quality

    Below 0.50 mean SQI over the last thirty beats, no auto-event is emitted. The floor sits at 0.50, not higher, because a PVC's own odd shape drags the rolling SQI down; too strict a gate would block the very beats it should catch. Under 0.50 the RR series is unreliable enough that a detector would invent variability that is not there.

    3. Prematurity + pause cross-check

    shape or timing

    The PVC compensatory-pause detector needs a pause that sums with the early RR to roughly 2 × baseline, plus either a QRS shape unlike the dominant sinus template or a beat at least 20 % early. Requiring shape alone missed PVCs the classifier had merged into sinus; the timing criterion recovers them. Breathing-linked sinus variation (8-10 % RR swing at the breathing rate) still falls below the bar and is filtered out.

    Pan-Tompkins stall recovery

    auto-recalibrate

    When the R-peak detector has not seen a beat in two seconds, the signal-peak estimate gently decays toward the noise estimate so the threshold relaxes. It also does a full threshold reset at the end of the ten-second warm-up so pairing artifacts cannot lock the detector high.

    Questions people actually ask

    Polar H10, PVCs, and what this app is not.

    Short, honest answers. The same wording is marked up for search engines, so if you found this page by asking one of these, you are in the right place.

    Does the Polar H10 record an ECG?

    The Polar H10 streams a raw single-lead ECG at 130 Hz over Bluetooth, but it does not store or display it on its own. RytmoECG receives that stream on your iPhone, draws it as a live ECG strip on real millimeter-paper scale, and analyzes every beat on-device.

    Can I count PVCs or track palpitations with a chest strap?

    Yes. RytmoECG flags premature ventricular contractions (PVCs), premature atrial contractions (PACs), couplets, bigeminy, pauses and irregular rhythm, and records an ECG clip around each one (fifteen seconds before it and at least ten seconds after) so you can see exactly what happened. It is a wellness tool for observing patterns over time, not a medical verdict.

    Is this a medical device or a Holter monitor?

    No. RytmoECG is a wellness app, not a medical device and not a certified Holter monitor. It does not diagnose, treat, or screen for any condition and gives no medical verdict. Think of it as a transparent, long-recording way to observe your own heart rhythm and export a PDF to show a clinician; a Holter-style experience, not a replacement for one.

    Does my ECG data leave my phone?

    No. Every algorithm runs on your iPhone. There is no cloud server and nothing is uploaded unless you explicitly tap Share to export a PDF or CSV.

    What do I need to use it?

    An iPhone on iOS 17 or later and a Polar H10 chest strap. The first three days are free with full access; the options after that are listed under Pricing.

    Can I export the raw signal for research?

    Yes. Any session exports as CSV (time, RR, HR, SQI per beat) or EDF, plus a PDF report. The data drops straight into Python, R, MATLAB or EDFbrowser.

    Pricing

    Three days free, then your choice.

    The download is free and you get 3 days of full access after the first install, no card required. After that you choose a monthly subscription, a yearly subscription, or a one-time lifetime purchase. Prices in your currency are shown in the app and in the App Store.

    Download for iPhone

    Where RytmoECG fails

    Plainly.

    • P-wave detection is unreliable on single-lead; we cannot separate atrial flutter from AF.
    • Paced rhythms are explicitly flagged as out of scope.
    • QTc on a noisy T-wave at 130 Hz is a trend marker, not clinical.
    • AF detector at F1 0.81 (CinC 2017 holdout); field accuracy depends on your signal quality.
    • None of this is medical advice. If something feels wrong, see a clinician.

    What RytmoECG will never do

    Promises.

    • Sell your data; the data never leaves the device unless you tap Share.
    • Talk to a server we control; there is none.
    • Score you against other users; comparisons are only with your own baseline.
    • Pretend a chest strap replaces a cardiologist.
    • Hide its math; every algorithm has a reference paper inside the app.

    RytmoECG is a wellness app, not a medical device and not a certified Holter monitor. It does not diagnose, treat, or screen for any condition and gives no medical verdict. Every result is a possible pattern for you to observe and, if you want, to show a clinician. If you have chest pain, shortness of breath, or persistent palpitations, contact emergency services or your physician.

    Get it

    Download RytmoECG.

    iPhone, iOS 17 or later. Requires a Polar H10 chest strap.

    App Store: coming soon

    Wellness app, not a medical device. Requires a Polar H10.